
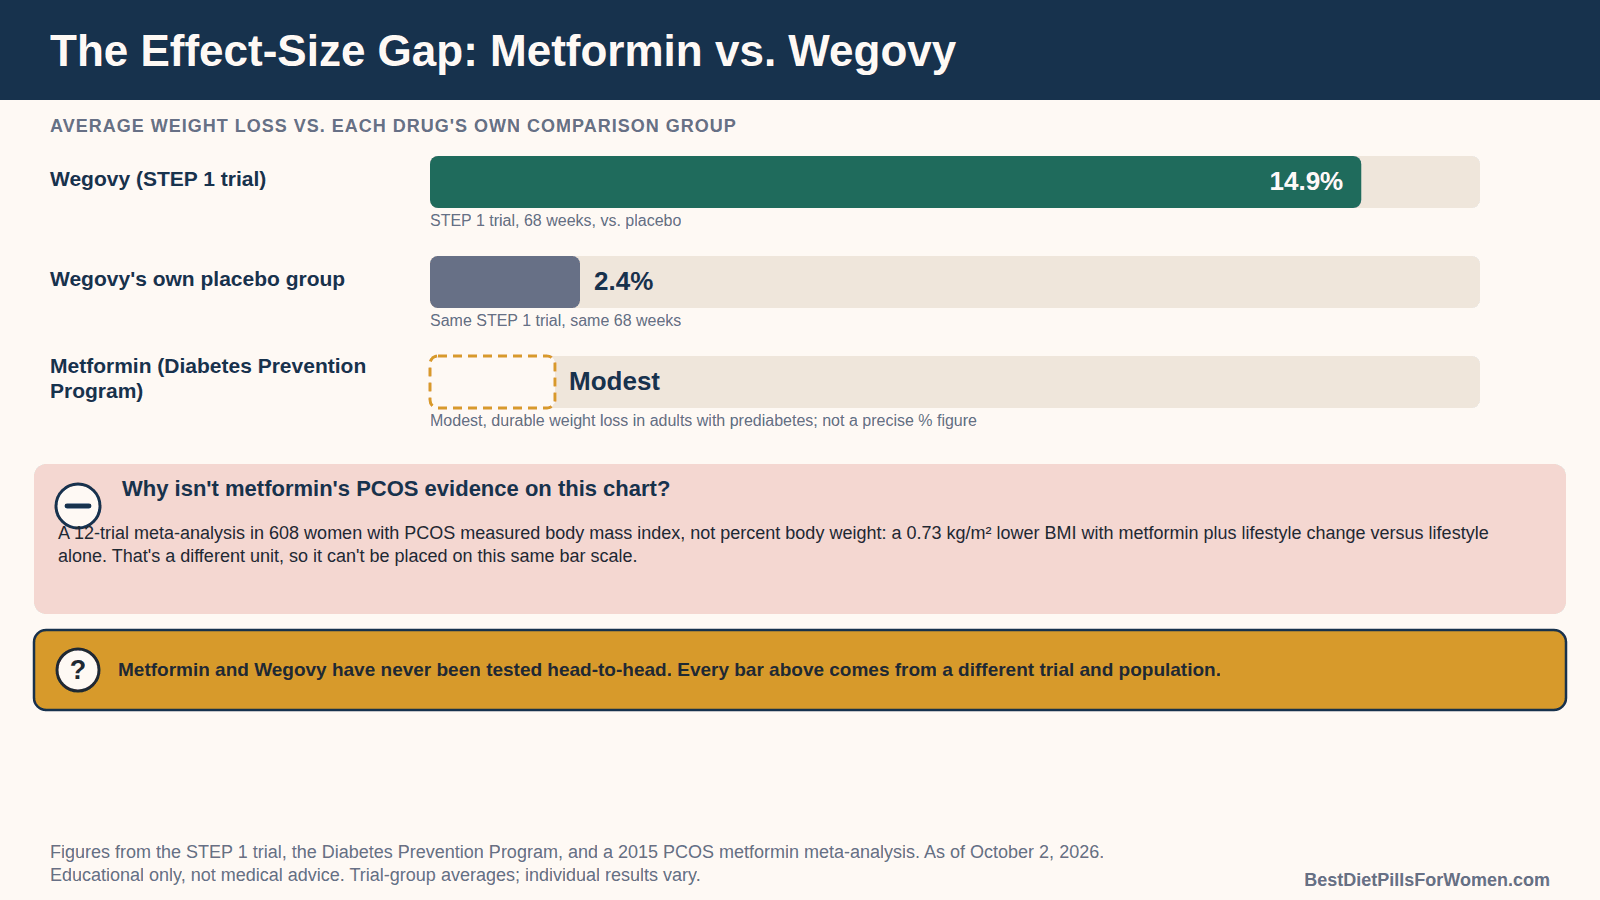
Metformin vs. Wegovy comes down to this: metformin is a decades-old, inexpensive type 2 diabetes pill that produces a small and inconsistent weight effect when it’s used off-label for that purpose, while Wegovy is a GLP-1 medicine that FDA specifically approved for chronic weight management. In Wegovy’s own pivotal trial, it produced roughly six times more average weight loss than metformin’s best-documented results, at a monthly price that can run into the hundreds or thousands of dollars rather than metformin’s few dollars.
That gap doesn’t make metformin useless, and it doesn’t make Wegovy automatically the right choice for every woman weighing this comparison. The two drugs aren’t approved for the same thing, they weren’t tested in the same kind of trial, and they show up in a woman’s life in very different ways: one is a cheap tablet many women already take for diabetes or PCOS, the other is a once-weekly injection with a list price that can run into the thousands of dollars a year. Comparing them fairly means being honest about what each one was actually built and studied to do, not just lining up two percentages and calling it a day.
This guide puts metformin and Wegovy side by side on the dimensions that matter for an actual decision: how each drug is thought to work, how much weight loss their own trials found, how their safety profiles differ, what each one costs right now, and who tends to be a more realistic fit for each. It’s built from current FDA prescribing information, the trials behind each drug’s approval or off-label use, and current pricing pages, not from a hands-on test of either medication. Nothing here is personalized medical advice, and nothing in this guide is a reason to start, stop or change a prescription medicine without a clinician who knows your own health history.
Metformin vs. Wegovy: The Short Answer
Start with the conclusions, then check them against the sections that back each one up.
The Direct Answer and How Sure We Are
Two separate questions are worth answering up front: what the evidence shows, and how confident we are in that evidence.
What’s the Real Difference Between Metformin and Wegovy for Weight Loss?
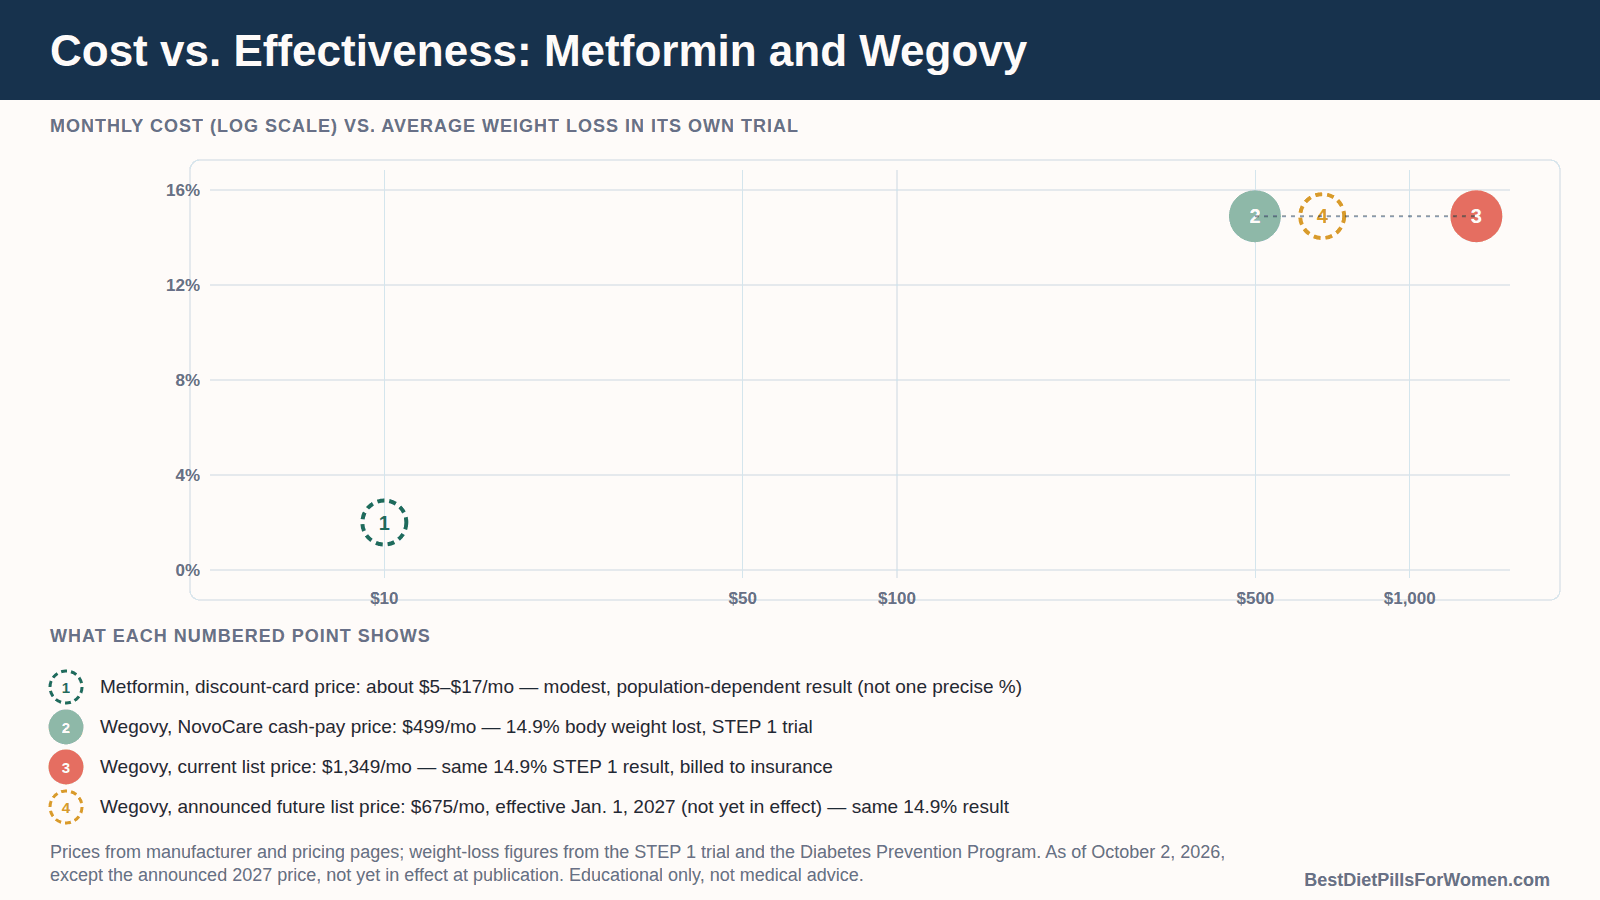
Metformin is a generic diabetes medicine that produces a small, inconsistent weight effect when used off-label; Wegovy is a once-weekly semaglutide injection that FDA approved specifically for weight management, and its pivotal trial found an average 14.9% body-weight loss at 68 weeks versus 2.4% on placebo. Cost tracks the same gap: metformin commonly runs $5 to $17 a month with a discount card, while Wegovy’s list price is $1,349 a month, though a direct cash-pay option brings that down to $499.
Neither drug is a stand-in for diet, activity or, for many women, an ongoing relationship with a prescriber who can adjust the plan over time.
How Sure We Are About That Answer
We’re highly confident about the direction and rough size of the effectiveness gap, since it comes from Wegovy’s own FDA-reviewed pivotal trial on one side and a mix of prediabetes, PCOS and general-population trials on metformin’s side, all pointing the same way. We’re less confident about a single precise number for metformin’s weight effect, because the trials behind it measured different populations, used different doses and endpoints, and in the case of general, non-diabetic adults, a widely cited systematic review found the evidence simply wasn’t strong enough to call it effective at all. Several of the older metformin sources behind this comparison were read through full prescribing labels and journal abstracts rather than complete peer-reviewed texts, since the full-text versions weren’t accessible in this research session; where that matters for a specific number, we say so.
We’re also confident that neither drug’s weight effect is a permanent, one-time event. Both require ongoing use to maintain their effect, and both sit inside a broader category of options; readers comparing Wegovy to other injectable or oral GLP-1 medicines may find our guide comparing semaglutide and tirzepatide useful for that separate, adjacent question.
How We Compared the Two Drugs
A fair comparison needs criteria that don’t quietly favor one side, so we set them out before looking at any results.
The Four Criteria We Used
We compared metformin and Wegovy on four dimensions: how each drug is thought to work, the quality and size of the human evidence behind its weight effect specifically, the realistic safety picture for each, and the practical trade-offs of cost and access. We left out brand marketing, influencer claims and social media buzz, none of which reflects clinical evidence. We also deliberately kept each drug’s approved, on-label purpose in view throughout, rather than judging metformin purely as a disappointing weight-loss drug, since that’s not the job it was built or approved to do in the first place.
What This Comparison Is and Isn’t
This is a desk-research comparison built from FDA prescribing information, published trial data, systematic reviews, and current pricing pages, not a hands-on test of either drug. We didn’t take, prescribe or lab-test anything described here, and nothing in this guide is personal experience. It’s also not a head-to-head clinical trial: metformin and Wegovy have never been tested against each other in the same study for weight loss, so every comparison here lines up separate trials with different populations, doses and durations. We say so explicitly wherever it affects how a number should be read, including in Table 1 below. It’s also not a ranking that declares one drug universally “better,” since the two aren’t competing for the same job in the first place; a fairer way to think about this guide is as a side-by-side look at two different tools that happen to get compared to each other constantly in real conversations between women and their prescribers.
| Dimension | Metformin | Wegovy (semaglutide injection) |
|---|---|---|
| FDA-approved for | Type 2 diabetes, as an adjunct to diet and exercise for glycemic control | Chronic weight management, and reducing major cardiovascular events in adults with established heart disease and obesity or overweight |
| Weight-loss indication | Off-label; not an FDA-reviewed use | On-label; the reason this form of semaglutide exists |
| Typical form | Oral tablet, once or twice daily, or an extended-release tablet once daily | Once-weekly subcutaneous injection; a once-daily 25 mg oral tablet version was separately approved in December 2025 |
| Key trial behind the weight numbers in this guide | A mix of sources: the Diabetes Prevention Program (prediabetes), a 12-trial PCOS meta-analysis, and a general-population systematic review | STEP 1, the pivotal trial behind the chronic-weight-management approval |
| Average weight result in that trial | Modest and inconsistent; often a few percent of body weight or not statistically significant, depending on the population | 14.9% of body weight lost on average, versus 2.4% on placebo, at 68 weeks |
| Most common side effects | Diarrhea, nausea, stomach upset, a metallic taste | Nausea, diarrhea, vomiting, constipation, abdominal pain, generally more frequent and more intense |
| Serious boxed warning | Lactic acidosis, a rare but potentially life-threatening buildup of lactic acid | Thyroid C-cell tumors in rodent studies; contraindicated with a personal or family history of medullary thyroid cancer |
| Typical monthly cost (cash, checked October 2026) | $5 to $17 with a free discount card at most major pharmacies | $499 a month through the manufacturer’s direct cash-pay pharmacy, or $1,349 a month at list price |
Table 1 method: figures are as reported in the FDA labels, trial summaries and pricing pages, read as of October 2, 2026. The metformin and Wegovy rows draw on different trials with different populations and durations, so this table is a side-by-side summary, not a head-to-head study result.
What Metformin and Wegovy Actually Are
Before comparing results, it helps to be clear about what each drug actually is, since that explains a lot of what follows.
Metformin: A Decades-Old Diabetes Pill Used Off-Label for Weight
Metformin has been a mainstay of diabetes care for decades, which is both its biggest strength and the reason its weight-loss evidence looks the way it does.
What Metformin Is Approved For
Metformin’s FDA-approved use is narrow: it’s indicated as an adjunct to diet and exercise to improve blood sugar control in adults with type 2 diabetes, and weight loss doesn’t appear anywhere in that approved indication. It’s sold as a generic under several brand names and formulations, including immediate-release tablets taken once or twice a day and extended-release tablets taken once daily, and it’s one of the most commonly prescribed medicines in the country for type 2 diabetes specifically because of its long track record and low cost. Major diabetes-care guidelines have for years named metformin as a typical first medicine to try for type 2 diabetes, before adding or switching to other drug classes, which is a large part of why so many women have already encountered it long before anyone raises the subject of weight specifically.
Why Clinicians Prescribe It Off-Label for Weight-Related Reasons
Clinicians prescribe metformin off-label in several situations where weight and insulin resistance overlap: for women with polycystic ovary syndrome (PCOS), where insulin resistance is common and metformin can improve metabolic markers and, modestly, weight; for people with prediabetes, where it’s used to delay or prevent progression to type 2 diabetes; and sometimes alongside antipsychotic medications known to cause weight gain. “Off-label” doesn’t mean unsafe or improper, and it’s an extremely common practice in medicine generally. It means FDA hasn’t reviewed clinical trial data specifically asking whether metformin works for weight loss as its own standalone goal, the way it has for Wegovy.
Typical starting doses run around 500 mg once or twice daily, with the dose increased gradually over several weeks toward a usual maintenance range of 1,500 to 2,000 mg a day, specifically to reduce the digestive side effects covered later in this guide’s Safety section. That slow-and-steady titration pattern, not a single large starting dose, is standard practice for metformin regardless of why it’s being prescribed.
A Note on Life Stage and Insulin Resistance
Insulin resistance doesn’t stay constant across a woman’s life, and that has some bearing on how each drug fits at different ages.
How Hormonal Changes Can Affect the Comparison
Insulin sensitivity commonly shifts around perimenopause and menopause, and many women notice changes in where fat is stored and how readily they gain weight during that transition, even without a formal PCOS or prediabetes diagnosis. That’s a reason some women in this life stage end up discussing metformin with a clinician even without a prior insulin-resistance diagnosis, though the strongest trial evidence for metformin’s weight effect still comes from women who do have PCOS or prediabetes specifically, not from midlife hormonal change on its own.
Why This Doesn’t Change the Core Comparison
None of this changes the basic effectiveness gap between the two drugs covered throughout this guide. It does mean that a woman’s reasons for considering metformin in the first place, independent of weight, are worth naming explicitly in a conversation with a clinician, since they shape how realistic a weight benefit actually is for her specific situation. Readers specifically navigating weight changes after 40 may also want our guide to weight loss pills for women over 40.
Wegovy: A GLP-1 Medicine Built for Weight Management
Wegovy belongs to a newer class of medicines that were studied, and approved, with weight loss itself as the primary question.
What Wegovy Is Approved For
Wegovy (semaglutide) is FDA-approved, alongside a reduced-calorie diet and increased physical activity, to reduce excess body weight in adults with obesity, or with overweight and a weight-related condition, and separately to reduce the risk of major cardiovascular events in adults with established cardiovascular disease and obesity or overweight. It’s also approved for some adolescents 12 and older with obesity. Unlike metformin, there’s no diabetes diagnosis required to qualify for Wegovy; weight itself, plus the BMI and comorbidity criteria in its label, is the basis for the prescription.
The Injection, the New Pill, and How Wegovy Relates to Ozempic
Wegovy and Ozempic are both brand names for semaglutide made by the same manufacturer, but they’re approved for different things and typically dosed differently: Ozempic is approved for type 2 diabetes, while Wegovy is approved for chronic weight management, and the two aren’t interchangeable just because they share an active ingredient. Historically, Wegovy meant only the once-weekly injection discussed throughout most of this guide, but FDA separately approved a once-daily 25 mg oral semaglutide tablet under the Wegovy name in December 2025, with an early trial readout putting its average weight loss somewhere in the 13% to 17% range depending on how people who stopped treatment early are counted in the analysis. This guide focuses on the original injectable Wegovy, since it has by far the longer track record and the most extensively reviewed trial data; readers specifically weighing GLP-1 options against each other may also want our comparison of semaglutide and tirzepatide. Both the injectable and oral forms of Wegovy require a prescription and the same upfront screening for thyroid-cancer history and other contraindications covered later in this guide’s Safety section; the delivery method changes convenience and, for some women, tolerability, but it doesn’t change the underlying drug class or its core safety considerations.
How Each Drug Is Thought to Work
The size of the weight-loss gap between these two drugs isn’t a coincidence. It traces directly back to how differently they act on the body.
Metformin’s Mechanism: Less Sugar Made, More Sugar Used
Metformin’s job, by design, is managing blood sugar, not appetite, and that distinction matters for what it can and can’t do for weight.
Hepatic Glucose Output and Insulin Sensitivity
Metformin’s primary actions are reducing how much glucose the liver releases into the bloodstream, known clinically as hepatic gluconeogenesis, and improving how sensitive muscle and other tissues are to insulin, so the body uses the glucose it already has more efficiently. It also modestly reduces how much glucose the intestines absorb from food. None of those actions directly targets hunger or appetite in the brain the way a GLP-1 medicine does.
Why This Mechanism Produces Only a Modest Weight Effect
Because metformin’s core mechanism is about glucose handling rather than appetite signaling, any weight change tends to be a secondary, smaller effect that shows up more reliably in people who start out with meaningful insulin resistance, like those with prediabetes or PCOS, than in the general population. That’s a proposed explanation consistent with the pattern across the trials in this guide, not a demonstrated cause-and-effect finding on its own; mechanistic plausibility and a confirmed clinical outcome aren’t the same thing, and the next section goes through exactly what the human trials found.
Why a Plausible Mechanism Isn’t the Same as a Confirmed Result
A clear biological mechanism, like metformin’s effect on the liver or semaglutide’s effect on appetite centers in the brain, explains why a weight change is plausible; it doesn’t by itself tell you how large that change will be in real people. That distinction matters most for metformin, where a sound, well-documented mechanism for improving insulin sensitivity hasn’t translated into a large or consistent weight-loss effect across the trials in the next section, which is exactly why this guide treats trial outcomes, not mechanism alone, as the deciding evidence.
Semaglutide’s Mechanism: Turning Down Hunger Signals
Semaglutide, the active ingredient in Wegovy, works through a completely different system, one built around appetite itself.
GLP-1 Receptors, Appetite, and the Brain
Semaglutide is a GLP-1 receptor agonist, meaning it mimics a natural gut hormone called glucagon-like peptide-1 and activates its receptors throughout the body, including in the hypothalamus and brainstem, the brain regions most involved in regulating hunger and fullness. That activation is thought to reduce hunger signals and increase feelings of satiety directly, which is why appetite reduction, not willpower, is the mechanism GLP-1 medicines are built around.
Slower Gastric Emptying and Its Trade-offs
Semaglutide also slows how quickly food leaves the stomach, which extends the feeling of fullness after a meal but is also the same mechanism behind the nausea, bloating and other digestive side effects covered later in this guide’s Safety section. The same action that makes a smaller meal feel satisfying is, for a meaningful share of users, the reason the drug is hard to tolerate at first.
Why the Dose Is Increased Slowly Over Several Months
Wegovy’s label calls for a gradual dose increase, starting at 0.25 mg weekly and stepping up roughly every four weeks toward the 2.4 mg maintenance dose used in STEP 1, specifically to give the body time to adjust to these gastric and appetite effects before reaching the full dose. Skipping ahead in the schedule, or restarting at a higher dose after a long gap off the medicine, is one of the more common reasons people experience worse side effects than the label’s own escalation plan is designed to prevent.
How Much Weight Loss Each Drug Actually Produces
This is where the two drugs diverge most sharply, and where it matters most to read the numbers in context rather than side by side as if they came from the same study.
Wegovy’s Trial Evidence
Wegovy’s approval rests on one of the largest, most specifically designed weight-loss trials in this comparison.
The STEP 1 Trial Numbers
In STEP 1, the pivotal trial behind Wegovy’s chronic-weight-management approval, 1,961 adults with obesity or overweight and a weight-related condition, with diabetes excluded, were randomly assigned to semaglutide 2.4 mg weekly or placebo, both alongside lifestyle counseling, for 68 weeks. The semaglutide group lost an average of 14.9% of body weight, compared with 2.4% on placebo, and 86.4% of the semaglutide group lost at least 5% of their starting weight, versus 31.5% on placebo. Overall adverse-event rates were similar between groups (89.7% versus 86.4%), but 4.5% of the semaglutide group stopped treatment specifically because of gastrointestinal side effects, compared with 0.8% on placebo.
How the Numbers Are Measured, and Why That Matters
Trial results like these can be reported two different ways: as a “treatment policy” estimate, which counts everyone as randomized whether or not they stayed on the drug the whole time, or as a “trial product” estimate, which reflects only people who stayed on treatment as planned. The 14.9% figure above is the treatment-policy number, the one that best reflects what a new user might realistically experience, including the portion of people who stop early; readers who see a higher published figure for the same trial are usually looking at the on-treatment estimate instead. That distinction isn’t a discrepancy to be suspicious of; it’s a standard part of how modern obesity trials are reported, and it’s worth knowing before comparing numbers across different sources.
STEP 1 wasn’t the only trial in Wegovy’s development program. Companion trials in the same STEP series tested semaglutide alongside more intensive behavioral support, in adults who also had type 2 diabetes, and as a withdrawal and maintenance question after a lower-dose run-in period, and they consistently found weight loss in a broadly similar double-digit percentage range, which is part of why regulators treated the effect as reproducible rather than a one-trial fluke. That withdrawal-focused trial specifically is worth returning to later in this guide, when discussing what happens if you stop treatment.
For side effects specifically, our dedicated guide to GLP-1 medicine side effects goes deeper into how to manage the gastrointestinal effects common across this drug class, including Wegovy.
Metformin’s Trial Evidence
Metformin’s weight data comes from a patchwork of trials that were mostly designed to answer a different question first.
The Diabetes Prevention Program and Prediabetes Data
The Diabetes Prevention Program, a large NIH-funded trial in adults with prediabetes, randomly assigned participants to intensive lifestyle changes, metformin, or placebo and followed them for an average of 2.8 years, with an extended follow-up study tracking many of the same participants for 10 years total. The lifestyle group lost substantially more weight early on, before some regain over time, while the metformin group’s weight loss was smaller but more durable, a pattern the extended follow-up still showed a decade later. We weren’t able to independently re-confirm the exact kilogram figures from the original trial report in this session, so treat the comparison as directionally reliable, modest and durable for metformin, larger but less durable for lifestyle, rather than as an exact number. The practical takeaway echoes the mechanism discussed earlier: metformin’s weight effect in this population wasn’t dramatic, but it didn’t evaporate either, which fits a drug that works through a steady metabolic change rather than a strong, direct effect on appetite.
PCOS-Specific Evidence
A systematic review and meta-analysis pooling 12 randomized trials in 608 women with PCOS found that metformin combined with lifestyle changes produced a modestly lower BMI than lifestyle changes alone, a mean difference of 0.73 kg/m² over about six months, along with improved menstrual cyclicity. Notably, the same review found that metformin by itself, without an added lifestyle component, wasn’t statistically different from lifestyle or placebo for weight or BMI at six months. That’s an important nuance: metformin’s modest weight benefit in PCOS trials shows up most clearly when it’s paired with lifestyle changes, not as a standalone effect. The improvement in subcutaneous fat and menstrual cyclicity matters in its own right for many women with PCOS, independent of the scale, since irregular cycles and androgen-related symptoms are often a bigger day-to-day concern than weight alone; that’s a meaningful reason metformin stays in PCOS care even where its weight evidence specifically is modest.
Why This Isn’t a Head-to-Head Comparison
Every number in the two subsections above comes from a different trial, and that difference matters more than a quick glance suggests.
Different Trials, Different Populations, Different Endpoints
STEP 1 studied adults with obesity or overweight who didn’t have diabetes, with weight loss as the trial’s primary outcome, measured as a percentage of starting body weight. The Diabetes Prevention Program studied adults with prediabetes, with diabetes prevention as the primary outcome and weight as a secondary measure. The PCOS meta-analysis pooled trials in a specific hormonal condition, measuring BMI in kilograms per square meter rather than percent body weight, over a much shorter typical follow-up. None of these trials put metformin and semaglutide in the same room, let alone the same randomized comparison.
What a Fair Reading of the Numbers Looks Like
The fair takeaway isn’t “semaglutide works and metformin doesn’t.” It’s that semaglutide’s trial evidence for weight loss specifically is large, consistent and was the basis of an FDA review built around that exact question, while metformin’s weight evidence is smaller, more population-dependent, and was mostly gathered as a secondary finding in trials built to answer a different question. Table 2 lays out each trial’s design side by side so the differences are visible rather than implied.
Why a Percentage Doesn’t Tell the Whole Story for Every Body Size
Percent-of-body-weight figures, like STEP 1’s 14.9%, translate into very different absolute numbers depending on where someone starts. For a woman who weighs 180 pounds, that works out to roughly 27 pounds; for a woman who weighs 240 pounds, the same percentage is closer to 36 pounds. Metformin’s smaller, often BMI-based results have the same quirk in reverse: a modest BMI change can represent a meaningful shift for someone already close to a healthy range, and a smaller fraction of total body weight for someone starting from a higher BMI. Neither direction makes one drug’s evidence more or less real; it’s a reason to think in terms of your own starting point rather than a single headline percentage from either drug’s trials.
| Study | Design | Population | Sample size | Duration | Intervention | Comparator | Outcome | Key limitation |
|---|---|---|---|---|---|---|---|---|
| STEP 1 | Randomized, double-blind, placebo-controlled | Adults with obesity, or overweight plus a weight-related condition; diabetes excluded | 1,961 (1,306 semaglutide, 655 placebo) | 68 weeks | Semaglutide 2.4 mg weekly plus lifestyle counseling | Placebo plus lifestyle counseling | -14.9% vs. -2.4% body weight; 86.4% vs. 31.5% lost at least 5% | Industry-funded; doesn’t include people with diabetes; 4.5% stopped early from GI side effects |
| Diabetes Prevention Program / DPPOS | Randomized, 3-arm, NIH-funded | Adults with prediabetes | About 3,234 enrolled; about 2,766 followed long-term | 2.8 years, with extended follow-up to 10 years | Metformin 850 mg twice daily | Intensive lifestyle change, and placebo | Modest, durable weight loss with metformin; larger early loss with lifestyle that partly reversed over time | Weight was a secondary outcome; population was selected for prediabetes, not obesity treatment |
| PCOS metformin meta-analysis | Systematic review and meta-analysis of randomized trials | Women with PCOS | 12 trials, 608 women | Mostly 6 months | Metformin, with or without lifestyle change | Lifestyle change, with or without placebo | BMI 0.73 kg/m² lower with metformin plus lifestyle; metformin alone not significantly different | Mostly short follow-up; metformin’s standalone effect wasn’t distinguished from the comparator |
| General-population metformin review | Systematic review | Adults with overweight or obesity, without diabetes or PCOS | 9 trials (screened from 57) | 15 days to 1 year | Metformin, 750 to 1,700 mg per day | Placebo or no treatment | Only 2 of 9 trials found a statistically significant weight-loss benefit | Reviewers judged the evidence insufficient; some trials ran as little as 15 days |
Table 2 method: figures are as reported in each cited trial, trial summary or systematic review, read as of October 2, 2026. Rows come from different trials with different populations, doses and durations; none of them tested metformin against semaglutide directly.
Why Real-World Results Often Look Smaller Than Trial Results
Clinical trial numbers describe what happened under closely monitored conditions, which isn’t quite the same as what happens once a medicine is used in everyday practice.
Adherence, Cost and Access Outside a Trial Setting
Trial participants received their medicine at no cost, were seen regularly by a study team, and had already agreed to stay on treatment for the trial’s full duration, none of which reliably carries over once a drug moves into routine prescribing. Outside a trial, Wegovy’s cost and side-effect burden lead some women to use it inconsistently, pause it, or stop earlier than planned, all of which tend to pull real-world average results below a pivotal trial’s headline number.
Why This Matters More for Wegovy Than for Metformin in Practice
This pattern tends to matter more for Wegovy specifically, since cost-driven gaps in use and side-effect-driven early discontinuation are both more common with it than with inexpensive, generally well-tolerated metformin. It’s a reason to treat STEP 1’s 14.9% as a best-case, closely supported outcome rather than a number every new user should expect automatically, without concluding the drug doesn’t work; it’s a reason to plan for the cost and tolerability side of treatment just as seriously as the expected result.
Safety and Side Effects Compared
Side effects and serious risks look different for these two drugs, and the pattern is more specific than “the stronger drug is the riskier one.”
Metformin’s Safety Profile
Metformin has one of the longest safety track records of any medicine still in common use, which makes its risk profile unusually well characterized.
Common Side Effects
Metformin’s most common side effects are digestive: diarrhea affected about 10% of people in clinical trials versus 3% on placebo, and nausea or vomiting affected about 7% versus 2%, with smaller shares reporting abdominal discomfort, bloating, gas, dizziness, headache or a metallic taste. These effects are usually most noticeable when starting the medicine or increasing the dose, and they often ease with time, with food, or with a switch to an extended-release formulation. Taking metformin with a meal rather than on an empty stomach, and starting at a lower dose before working up to a full prescribed amount, are both standard, label-consistent ways prescribers try to reduce how disruptive these early side effects feel.
Serious Risks: Lactic Acidosis and Vitamin B12 Deficiency
Metformin carries a boxed warning for lactic acidosis, a rare but potentially life-threatening buildup of lactic acid in the blood, with risk concentrated in people with significant kidney impairment, liver disease, heavy alcohol use, certain other medical conditions, or situations like major surgery or an imaging procedure that uses contrast dye. Separately, about 7% of people in the trials behind metformin’s label had a measured drop in vitamin B12 levels, which is why current labeling recommends periodic blood testing, including vitamin B12 levels every two to three years, for people on long-term metformin therapy.
Wegovy’s Safety Profile
Wegovy’s side-effect pattern is dominated by the same gastrointestinal system its mechanism works through, generally at a higher intensity than metformin’s.
Common Side Effects
In Wegovy’s clinical trials, the most common side effects, each affecting at least 5% of users, were nausea (44%), diarrhea (30%), vomiting (24%), constipation (24%), abdominal pain (20%), headache (14%), fatigue (11%), indigestion (9%), dizziness (8%), abdominal bloating (7%) and belching (7%). For comparison, metformin’s most common side effects affect a noticeably smaller share of users and a narrower symptom list, which is a meaningful, if less dramatic, part of this comparison’s safety picture alongside the weight-loss numbers themselves. Low blood sugar occurred in about 6% of people with type 2 diabetes using the drug, though hypoglycemia isn’t typically a concern for someone using Wegovy without diabetes. These digestive effects tend to be worst during the first several weeks of each dose increase and then settle somewhat once the body adjusts, which is the practical reason behind the slow titration schedule described earlier in this guide’s mechanism section; eating smaller, lower-fat meals and stopping before feeling completely full are commonly suggested, label-consistent ways to make the adjustment period more tolerable.
Serious Risks: Thyroid Tumor Warning, Pancreatitis, and Gallbladder Disease
Wegovy carries a boxed warning because semaglutide caused thyroid C-cell tumors in rodent studies at clinically relevant exposures; whether that risk applies to humans remains unknown, and the drug is contraindicated for anyone with a personal or family history of medullary thyroid carcinoma or multiple endocrine neoplasia syndrome type 2. Acute pancreatitis has also been reported with GLP-1 medicines as a class, and gallbladder disease is a documented concern: gallstones occurred in 1.6% of Wegovy users versus 0.7% on placebo, and gallbladder inflammation in 0.6% versus 0.2%. FDA’s label also notes a need to monitor kidney function in people who develop severe gastrointestinal symptoms, since dehydration from persistent vomiting or diarrhea can affect the kidneys.
Who Needs Extra Caution With Either Drug
Beyond each drug’s own warnings, a few situations call for a specific conversation before starting either one.
Kidney Function, Contrast Dye, and Surgery
Metformin’s lactic acidosis risk is tied closely to kidney function: current labeling advises against starting it when estimated kidney function (eGFR) is between 30 and 45, and it’s contraindicated outright below an eGFR of 30, with a temporary pause often recommended around procedures using contrast dye or major surgery. Wegovy doesn’t carry the same kidney-specific contraindication, but severe, persistent vomiting or diarrhea from the drug can affect kidney function indirectly, which is its own reason to contact a prescriber if GI side effects become severe rather than waiting them out. A baseline kidney-function blood test before starting either drug, and periodic rechecks after, is standard practice precisely because both drugs interact with kidney health in different but meaningful ways.
Pregnancy, Breastfeeding, and Family-Building Plans
Wegovy isn’t recommended during pregnancy, and current guidance is to stop it at least two months before a planned pregnancy, based on how long the drug takes to clear the body; data in human pregnancy remains limited. Metformin has a longer track record around pregnancy, including use for gestational diabetes in some cases, but any use in pregnancy or while breastfeeding, for either drug, needs individualized guidance from an obstetric provider rather than a general comparison like this one. For a woman actively trying to conceive, the practical planning timelines are genuinely different between the two drugs, which is itself a reason to raise family-building plans early in any conversation about starting either one, not after a prescription is already written.
Practical Steps If Side Effects Become Hard to Tolerate
Knowing which side effects warrant a phone call, versus which ones are an expected part of adjusting to either drug, makes the early weeks of either medicine considerably less stressful.
When to Call a Prescriber Right Away
Severe abdominal pain that doesn’t ease, especially pain that radiates to the back, along with persistent vomiting, unusual muscle pain with weakness or breathing difficulty, or vision changes, are reasons to contact a prescriber promptly rather than waiting to see if things improve on their own, since they can signal pancreatitis, gallbladder problems, or, rarely, lactic acidosis depending on which drug is involved. Severe allergic reaction symptoms, like swelling of the face or throat or difficulty breathing, warrant emergency care immediately with either medicine.
When a Dose Adjustment, Not Stopping, Is the Usual Next Step
For the more common, milder gastrointestinal side effects covered above, from nausea to stomach upset, the typical next step a prescriber considers is slowing down a dose increase, holding at a current dose for longer before advancing, or adjusting how a dose is taken relative to meals, rather than stopping the medicine outright. Stopping either drug abruptly on your own, without talking to the prescriber who started it, skips the chance to solve a tolerability problem that often has a simpler fix than discontinuing treatment altogether.
| Drug | Most common side effects | Frequency (drug vs. comparator) | Serious risk to know |
|---|---|---|---|
| Metformin | Diarrhea, nausea/vomiting, stomach discomfort, metallic taste | Diarrhea about 10% vs. 3%; nausea/vomiting about 7% vs. 2% | Lactic acidosis (rare, boxed warning); vitamin B12 deficiency with long-term use |
| Wegovy | Nausea, diarrhea, vomiting, constipation, abdominal pain | Nausea 44%; diarrhea 30%; vomiting 24%; constipation 24%, each vs. a lower placebo rate in STEP 1 | Thyroid C-cell tumor warning (boxed); pancreatitis; gallbladder disease (gallstones 1.6% vs. 0.7%) |
Table 3 method: figures as reported in each drug’s current FDA prescribing information and, for Wegovy’s GI discontinuation context, the STEP 1 trial, read as of October 2, 2026. The two rows come from different trial programs and aren’t a head-to-head safety comparison.
Drug Interactions and Combining the Two
What a woman is already taking changes the calculus for either of these drugs, and the two have different interaction profiles worth flagging separately.
What Can Interact With Metformin
Metformin’s interactions mostly run through the kidneys, the liver, and other diabetes medicines.
Alcohol, Contrast Dye, and Other Diabetes Medicines
Heavy alcohol use raises the risk of lactic acidosis with metformin, and the drug is often paused temporarily around imaging procedures that use iodinated contrast dye or around major surgery, since both can affect kidney function at least briefly. Combining metformin with insulin or certain other diabetes medicines, like sulfonylureas, can increase the risk of low blood sugar, which is a reason blood sugar monitoring matters more when multiple diabetes medicines are used together. Metformin is also commonly held temporarily before and after certain scans or procedures that use iodine-based contrast dye, specifically because of the lactic acidosis risk tied to any short-term change in kidney function around those procedures; a radiology team or prescriber will typically flag this automatically, but it’s worth mentioning metformin use whenever a contrast-based scan is being scheduled.
Supplements and Over-the-Counter Products Worth Flagging
Because metformin can modestly lower vitamin B12 absorption over time, a woman taking it long-term has a specific reason to mention any B12 or multivitamin supplement she’s using, and to bring up any other supplement that affects blood sugar, since the combined effect isn’t always predictable from either product’s label alone.
What Can Interact With Wegovy
Wegovy’s main interaction concern is less about specific drug combinations and more about how it changes the way other medicines are absorbed.
Oral Medications and Delayed Gastric Emptying
Because semaglutide slows gastric emptying, it can change how quickly other oral medications are absorbed, which matters most for drugs with a narrow safety margin or that need to reach a precise blood level quickly. A pharmacist is best positioned to review a woman’s complete medication list against this specific mechanism before she starts Wegovy. This is also a reasonable, specific question to raise if you’re using any form of hormonal birth control, since absorption timing is exactly the kind of detail a pharmacist can check against your particular product; this guide isn’t the place to resolve that question for you, but it’s worth asking rather than assuming nothing has changed.
Insulin, Sulfonylureas, and Hypoglycemia Risk
In people who also have type 2 diabetes, combining Wegovy with insulin or a sulfonylurea raises the risk of hypoglycemia, which is why those combinations typically call for closer blood sugar monitoring and, sometimes, a dose adjustment to the other diabetes medicine. This isn’t usually a concern for someone using Wegovy for weight management alone, without diabetes or those other medicines on board.
Can Metformin and Wegovy Be Prescribed Together?
The “versus” framing of this comparison doesn’t reflect how these two drugs are often actually used in practice.
Why This Combination Already Happens in Practice
For a woman with type 2 diabetes who also has obesity, it’s common for a prescriber to keep metformin as a foundation for blood sugar control while adding a GLP-1 medicine, whether that’s Wegovy specifically for weight management or a diabetes-indicated semaglutide product, for additional weight and glycemic benefit, since the two drugs work through different mechanisms rather than competing for the same biological target. That combination reflects standard practice in diabetes and obesity care, not an unusual or off-label pairing of two unrelated drugs. Clinical treatment guidelines for type 2 diabetes have increasingly favored layering medicine classes with different mechanisms, rather than pushing a single drug to its maximum dose before adding anything else, which is part of the broader context behind why this specific combination has become common. From a prescriber’s point of view, metformin’s low cost and long safety record make it a sensible foundation to build on, while a GLP-1 medicine added on top addresses both the remaining blood sugar goal and weight in a way metformin alone usually can’t reach for a given patient.
What That Doesn’t Mean for a Reader Comparing the Two
None of that changes the core comparison for a reader without diabetes who’s weighing metformin against Wegovy as two separate paths to weight loss on their own. For that specific decision, the evidence gap described throughout this guide still applies, and combining the two isn’t something to try on your own initiative; it’s a decision for a prescriber based on a full picture of your health, not a do-it-yourself stacking strategy. If you don’t have diabetes and your goal is purely weight management, the relevant comparison for you really is the one this guide walks through end to end, not a combination most prescribers wouldn’t reach for outside a diabetes diagnosis in the first place.
Cost and Access
Few parts of this comparison are as lopsided as price, and the gap has real consequences for who can realistically use each option long-term.
What Metformin Costs
Metformin’s price is, by a wide margin, the cheapest line item in this entire comparison.
Cash Price and Insurance Coverage
With a free discount card, metformin commonly costs $5 to $17 a month for a standard 60-tablet, 500 mg supply at major pharmacy chains, and it’s typically covered by insurance, including Medicare and Medicaid, as a low-tier generic with a copay of $0 to $10. A small number of pricing pages list an uninsured, no-discount “average retail” price well over $100 a month; that figure appears to reflect a sticker price few people actually pay rather than a typical real-world cost, since a discount card or standard insurance usually brings the price down dramatically. Medicaid programs, which cover a meaningful share of reproductive-age women, typically place metformin on their lowest-cost generic tier as well, often with no copay or a copay of just a few dollars, though exact terms vary by state program.
Why It’s So Inexpensive
Metformin has been available as a generic medicine for decades, with many manufacturers producing it and no patent protection left to support a premium price, which is the main reason its price floor sits so far below almost every other medicine in this comparison. That long track record and low cost are exactly why it remains a first-line diabetes medicine even as newer, pricier options have entered the market. Several large retail pharmacy chains also include generic metformin on their own lowest-tier discount generic drug lists, independent of any manufacturer coupon or insurance plan, which is part of why its real-world price rarely resembles an uninsured “list price” the way a newer brand-name drug’s does.
What Wegovy Costs
Wegovy’s price sits at the opposite end of the spectrum, and the picture is more complicated than a single number.
List Price, the Cash-Pay Program, and the Coming Price Cut
Wegovy’s current list price is $1,349 a month, the figure typically used for insurance billing, but Novo Nordisk’s NovoCare Pharmacy offers a direct cash-pay price of $499 a month for all dose strengths, available to anyone paying out of pocket regardless of insurance status. Separately, Novo Nordisk announced in February 2026 that it will cut Wegovy’s list price to $675 a month effective January 1, 2027, a change that hadn’t yet taken effect as of this guide’s October 2026 publication date and should be reconfirmed before relying on it. Our guide to Wegovy’s current cost and coverage options goes deeper into the various pricing paths.
Insurance Coverage Hurdles and Prior Authorization
Even when a plan covers Wegovy, coverage usually depends on meeting specific diagnosis and prior-authorization requirements, and Novo Nordisk has stated that roughly 90% of commercially insured, eligible patients using its savings card pay $0 to $25 a month, but that figure applies only to people whose specific plan already covers the drug. Many commercial plans, and a large share of Medicare Part D plans, still exclude anti-obesity medications from coverage entirely or require documentation of a weight-related condition and a prior unsuccessful weight-loss attempt before approving it, so a woman considering Wegovy should check her own plan’s specific terms rather than assume the savings-card figure applies to her. Wegovy’s separate approval to reduce cardiovascular risk in people with established heart disease and obesity or overweight has started to change some insurers’ coverage decisions, since a cardiovascular indication is sometimes treated differently from a weight-management-only indication for coverage purposes, so it’s worth specifically asking whether that distinction applies to your plan if you have a relevant heart-health history. Pharmacy benefit managers and individual employer plans also change their formulary rules from year to year, sometimes more than once within the same plan year, so a coverage answer you received six months ago isn’t a reliable guide to what’s true today without a fresh check.
| Option | Typical monthly cost | Annual cost at that price | Typical coverage |
|---|---|---|---|
| Metformin, with a discount card | $5–$17 | $60–$204 | Usually a Tier 1 generic; often $0–$10 copay with insurance |
| Wegovy, NovoCare direct cash-pay | $499 | $5,988 | Self-pay program; bypasses insurance entirely |
| Wegovy, current list price | $1,349 | $16,188 | Billed to insurance; copay depends on plan and prior authorization |
| Wegovy, announced future list price (effective January 1, 2027) | $675 (not yet in effect) | $8,100 (projected) | Same coverage caveats as current list price |
Table 4 method: prices as listed on manufacturer and pricing pages read as of October 2, 2026; annual figures are this guide’s own multiplication of the listed monthly price by 12 and assume no change in price, dose or coverage across the year, which real-world use rarely matches exactly.
Who Each Option Might Realistically Fit
Everything above is about the two drugs in the abstract. This section is about which one, if either, tends to make more sense for a specific kind of situation, recognizing that the honest answer for a lot of women isn’t a clean either-or but a sequence of trade-offs weighed against a specific budget, health history and goal.
When Metformin Might Be the More Realistic Starting Point
Metformin’s narrower, gentler effect fits some situations better than a far stronger but far more expensive option would.
PCOS, Prediabetes, and Insulin Resistance
A woman with PCOS, prediabetes or another insulin-resistance-related condition is in the population where metformin’s modest weight effect is most consistently documented, and where the drug is already likely to be part of her care for reasons beyond weight alone, including cycle regulation and diabetes prevention. For her, metformin isn’t really “instead of” a weight-loss drug; it’s a treatment for an underlying condition that happens to carry a small weight benefit too. Our deeper guide to the best weight loss pills for PCOS covers how metformin fits alongside other PCOS-specific options, including other insulin-sensitizing supplements like berberine, which some women compare to metformin because of its similar, modest proposed mechanism.
When Budget or Access Rules Out a GLP-1 Medicine
For a woman without insurance coverage for weight-management drugs, or for whom even the $499 cash-pay price for Wegovy isn’t realistic, metformin’s low cost and wide insurance coverage make it a far more accessible option, even knowing upfront that its weight effect will likely be modest. A smaller, well-tolerated and affordable change is a reasonable starting point for some people, as long as the expectation is set accurately from the start rather than borrowed from Wegovy’s very different trial results. It’s also worth revisiting over time rather than treating as a permanent decision; insurance coverage, personal finances and a woman’s own health picture can all change, and a drug that wasn’t realistically accessible at one point sometimes becomes a reasonable option to raise again later.
When Wegovy Might Be the More Realistic Starting Point
Wegovy was studied in, and approved for, a fairly specific population, and that population is the clearest fit for the drug.
BMI and Weight-Related Health Conditions
Wegovy is approved for adults with a BMI of 30 or higher, or 27 or higher with a weight-related condition such as high blood pressure, high cholesterol, type 2 diabetes or sleep apnea, which is also the population most insurers use as a baseline for prior authorization. A woman in that group, especially one with a comorbidity that a meaningful weight loss could improve, is the population STEP 1’s strongest results actually describe.
When a Larger, Faster Result Matters Most
For someone whose main goal is the largest, most consistent weight loss covered in this guide, nothing in metformin’s evidence base comes close to STEP 1’s results, and that gap alone is often the deciding factor once cost and access aren’t limiting. Anyone with a personal or family history of thyroid cancer, a history of pancreatitis, or a current or planned pregnancy has a specific, documented reason from this guide’s Safety section to raise that history before starting Wegovy rather than after. A woman who already has type 2 diabetes and is weighing Wegovy against the diabetes-indicated version of the same active ingredient may also want our separate comparison of Ozempic and Wegovy, since the dosing and approved indications differ even though the drug itself doesn’t.
What Happens If You Stop
Neither drug’s effect is something to assume will simply continue on its own once treatment ends, and that’s worth thinking through before starting either one, not only after stopping.
Weight Changes After Stopping Wegovy
Clinical experience and trial extension data with GLP-1 medicines generally show that appetite tends to return toward its prior baseline once the drug is stopped, and a meaningful share of the weight lost during treatment tends to come back over the following months without continued use or significant lifestyle changes to offset it. That pattern is a direct consequence of the drug’s appetite-suppressing mechanism rather than a flaw unique to any one person’s willpower. A dedicated maintenance trial within the STEP program tested this directly, randomizing people who’d already lost weight on semaglutide to either continue it or switch to placebo, and it found the same pattern: the placebo group regained a substantial share of the weight they’d lost, while those who continued treatment largely held their results, which is the clearest evidence in this guide that Wegovy’s benefit depends on continued use rather than permanently resetting the body’s baseline.
Weight Changes After Stopping Metformin
Metformin’s weight effect, being smaller and more tied to underlying insulin sensitivity, doesn’t carry the same dramatic “rebound” pattern, partly because there’s less weight change to begin with; the Diabetes Prevention Program’s extended follow-up data describe a loss that was modest but fairly durable over a 10-year window while participants stayed on the medicine, rather than a large early loss followed by rapid regain.
Frequently Asked Questions About Metformin and Wegovy
A few questions come up often enough in this comparison to answer directly, even where the answer repeats a point made earlier in more depth.
Effectiveness and Mechanism
Is Wegovy Always More Effective Than Metformin for Weight Loss?
In the trials behind each drug, yes, by a wide margin, but “always” is too strong a word for any individual person’s experience. STEP 1 found an average 14.9% body-weight loss with semaglutide, while metformin’s own best-documented weight results are smaller and more population-dependent. Individual responses vary within every drug category, and a small share of people see less benefit than the average, or more side effects than they can tolerate, from even the strongest option in a given comparison.
Why Does Metformin Cause Less Weight Loss Than Wegovy?
Metformin’s core mechanism targets glucose handling in the liver and muscles, not appetite, so any weight effect tends to be a smaller, secondary byproduct rather than the drug’s main action; semaglutide, by contrast, directly targets hunger and fullness signals in the brain, which is a more powerful lever for weight specifically.
Can Metformin Help With Weight Loss If I Don’t Have Diabetes or PCOS?
Possibly, but the evidence is weaker here than in those two groups. A systematic review in adults without diabetes or PCOS found only 2 of 9 trials showed a statistically significant weight-loss benefit, leading reviewers to call the evidence insufficient for that specific population. That doesn’t mean it can’t help any individual person, but it does mean the odds, based on available trials, aren’t as favorable as they are for someone with insulin resistance already driving the prescription.
How Long Does It Take to See Results on Either Drug?
In STEP 1, semaglutide’s weight loss built up gradually over the full 68 weeks rather than appearing in the first few weeks, tracking the slow dose-escalation schedule described earlier in this guide. Metformin’s modest effect, where it occurs, also tends to show up over months rather than weeks. Neither drug is designed to produce a fast, early result, and expecting one is a common source of disappointment with both.
Safety and Who Should Be Cautious
Is Wegovy Safe to Use Long-Term?
Wegovy’s safety data extends through its approval trials and post-marketing monitoring, and most users tolerate it without the boxed-warning-level risks, but “long-term safe” isn’t the same as “risk-free for everyone.” Anyone with a personal or family history of medullary thyroid cancer shouldn’t use it at all, and anyone with a history of pancreatitis or gallbladder disease should discuss that history with a prescriber before starting. Ongoing use should be reassessed periodically with a prescriber rather than treated as a permanent, unchanging prescription.
Does Metformin Cause Vitamin Deficiencies?
It can lower vitamin B12 levels over time; about 7% of people in the trials behind its label had a measured drop in B12. Current labeling recommends checking vitamin B12 levels periodically, typically every two to three years, for people on long-term metformin therapy, which is a simple, low-cost way to catch the issue before it causes symptoms like fatigue or nerve-related numbness.
Who Shouldn’t Take Wegovy or Metformin?
Wegovy shouldn’t be used by anyone with a personal or family history of medullary thyroid carcinoma or multiple endocrine neoplasia syndrome type 2, and it isn’t recommended during pregnancy. Metformin is contraindicated at an estimated kidney function (eGFR) below 30 and isn’t recommended to start between 30 and 45, and it carries extra caution around heavy alcohol use, significant liver disease, and procedures involving contrast dye. Both lists are a starting point for a conversation with a prescriber, not a complete substitute for one.
Cost, Access, and Practical Decisions
Why Is Wegovy So Much More Expensive Than Metformin?
Metformin has been a generic medicine for decades with no patent protection and many manufacturers competing on price, while Wegovy is a newer, patent-protected brand-name biologic-adjacent medicine still under exclusive manufacturing rights, which is the main structural reason for the price gap rather than any difference in manufacturing cost alone.
Does Insurance Cover Wegovy If I Don’t Have Diabetes?
It depends entirely on your specific plan. Wegovy doesn’t require a diabetes diagnosis to be prescribed, since its approval is for weight management and cardiovascular risk reduction, but many commercial plans and a large share of Medicare Part D plans still exclude anti-obesity medications from coverage or require prior authorization and documentation of a weight-related condition. Checking your plan’s specific formulary and prior-authorization rules before assuming coverage either way is worth the phone call.
Can I Ask My Doctor for Metformin Instead of Wegovy to Save Money?
You can certainly raise it as an option, and for some women, especially those with PCOS, prediabetes or insulin resistance, it’s a reasonable starting conversation. What a prescriber can’t responsibly do is promise metformin will produce anything close to Wegovy’s trial-documented results, since the evidence behind the two drugs for weight loss specifically isn’t comparable in size or consistency. The honest framing for that conversation is “a cheaper, gentler option with modest expectations” rather than “a budget version of the same result.”
Can I Switch From Metformin to Wegovy, or Try One After the Other?
Switching, or trying one option after the other doesn’t produce the expected result, is a reasonable and common path, not a sign that an earlier choice was wrong. A prescriber who knows why metformin didn’t work as hoped, whether that’s tolerability, dose, or simply belonging to a population where its weight evidence is weak to begin with, can use that information to decide whether Wegovy, a different medicine, or a non-drug approach makes more sense next.
The Bottom Line on Metformin vs. Wegovy
Everything in this guide points toward the same underlying answer, worth stating plainly before you decide anything.
What the Total Evidence Means for You
The gap between these two drugs isn’t a marketing difference. It’s a direct reflection of what each one was built, studied and approved to do.
The Biggest Realistic Benefit of Each
Wegovy’s biggest realistic benefit is the largest, most consistently documented weight loss in this entire comparison, backed by a trial FDA reviewed specifically for a weight-management approval. Metformin’s biggest realistic benefit is accessibility: it’s inexpensive, widely covered by insurance, and already has a well-established role in treating conditions like PCOS and prediabetes where a modest weight benefit comes alongside its primary purpose.
The Biggest Limitation or Safety Concern of Each
Wegovy’s biggest limitation is cost and access, since even its cash-pay price runs close to $500 a month and its list price is nearly three times that, with insurance coverage depending heavily on a woman’s specific plan. Metformin’s biggest limitation is simply that it isn’t built to produce large weight loss for most people, and anyone expecting Wegovy-level results from it is likely to be disappointed. On the safety side, Wegovy’s thyroid-tumor boxed warning and gallbladder and pancreatitis risks sit alongside metformin’s rarer but more acute lactic-acidosis risk and its subtler, long-term vitamin B12 concern; neither drug is risk-free, and the two risk profiles simply look different rather than one being clearly safer than the other across every situation. Weighing those risk profiles against your own health history, not just against each other in the abstract, is the part of this decision a general comparison genuinely can’t do for you.
A Rational Next Step
None of this is a reason to assume one drug is simply right and the other simply wrong. It’s a reason to be specific about what you’re actually choosing between.
Questions for a Clinician
If Wegovy is on the table, ask what your specific plan’s prior-authorization and continuation requirements actually are, whether anything in your personal or family history, especially thyroid cancer or pancreatitis, might rule it out, and what a realistic timeline for results looks like for someone with your starting point. If you’re leaning toward metformin, ask directly what weight result is realistic for your specific situation, since the honest answer, based on the evidence in this guide, is usually “modest” rather than “comparable to a GLP-1 medicine.” Either way, our broader guide to the best weight loss pills for women and our comparison of prescription and OTC weight loss pills cover more of the options beyond just these two. Bring this guide’s tables with you if it’s useful; a prescriber working from the same specific numbers you’ve already seen can usually have a more efficient, more productive conversation than one starting from scratch.
What to Re-Check Before You Spend Money
Prices, insurance prior-authorization rules, and FDA label updates for both drugs can change within weeks of when this guide was checked. Before spending money on either option, reverify current pricing directly with the manufacturer or your pharmacy, confirm your specific plan’s current coverage rules for Wegovy, and ask your prescriber whether anything in your personal health history has changed since you last discussed either medicine. The drug with the strongest evidence for weight loss specifically isn’t automatically the right or only choice for every woman’s budget and health picture, and the drug with the lowest price isn’t automatically the wrong one either. The honest answer, for almost everyone reading this, is that the choice deserves the same specific, evidence-based questions this guide just walked through, not a blanket rule in either direction. Metformin and Wegovy will likely keep getting compared to each other in casual conversation precisely because they’re both common, well-known names in weight-related care, but a fair comparison, as this guide has tried to show throughout, means holding onto the fact that they were built for different jobs even as they sometimes get asked to do the same one.
Related Reading
Sources
These are the main sources behind this guide, chosen because they are the ones to check first for current facts. Labels, prices and trial summaries change, so confirm the latest version before you make decisions.
- U.S. Food and Drug Administration. WEGOVY (semaglutide) injection, for subcutaneous use — prescribing information, label archive version 215256s011 (2024 posting; newer archived versions, including 215256s026 from 2025 and 215256s029 through s031 from 2026, exist and should be checked for the current approved text before publication). https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/215256s011lbl.pdf
- U.S. Food and Drug Administration. FORTAMET (metformin hydrochloride extended-release tablets) — prescribing information, label archive version 021574s032 (2026 posting). Other metformin products carry the same boxed warning and core safety language. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/021574s032lbl.pdf
- American College of Cardiology. Clinical Trial Summary: STEP 1 — Semaglutide Treatment Effect in People With Obesity, summarizing results originally reported in the New England Journal of Medicine (2021). https://www.acc.org/Latest-in-Cardiology/Clinical-Trials/2021/02/18/19/23/STEP-1
- Medical News Today, summarizing 10-year follow-up results of the NIH-funded Diabetes Prevention Program and Diabetes Prevention Program Outcomes Study (DPP/DPPOS). Read as a secondary summary; the original trial reports were not independently re-read in this session. https://www.medicalnewstoday.com/articles/169082
- PubMed. Metformin and lifestyle modification in polycystic ovary syndrome: systematic review and meta-analysis (abstract read; PMID 26060208). https://pubmed.ncbi.nlm.nih.gov/26060208/
- Systematic review of metformin as a treatment for overweight and obese adults without diabetes or PCOS, published in Annals of Family Medicine (2005). https://www.annfammed.org/content/3/5/457
- Mayo Clinic Diet. How Does Semaglutide Work? https://diet.mayoclinic.org/us/blog/2024/how-does-semaglutide-work/
- Managed Healthcare Executive. Novo Nordisk Lowers Wegovy Price for Cash-Paying Patients (March 5, 2025). https://managedhealthcareexecutive.com/view/novo-nordisk-lowers-wegovy-price-for-cash-paying-patients
- Novo Nordisk. News release on list-price changes for Wegovy, Ozempic and Rybelsus effective January 1, 2027 (February 24, 2026). https://www.novonordisk.com/news-and-media/news-and-ir-materials/news-details.html?id=916504
- SingleCare. Metformin Hcl Coupons & Prices (cash and discount-card price listing). https://www.singlecare.com/prescription/metformin

